When Antidepressants Aren't Working: Your Options in Denver
By Charles Shuman • October 12, 2026

Quick Answer: If two or more antidepressants haven't helped enough, that's called treatment-resistant depression, and it's common. The next step isn't necessarily another prescription. It's a thorough review of whether the diagnosis is correct, whether the doses and durations were adequate, and whether something else is getting in the way. From there, the options include changing or combining medications, adding therapy, or moving to TMS, Spravato, or ketamine.
Being on your third antidepressant and still feeling the same is demoralizing. It can start to feel like the problem is you rather than the treatment. It usually isn't. Depression is not one condition with one mechanism, and the first medication someone tries is an informed guess, not a precision match.
Here's how a psychiatrist approaches it when the usual approach hasn't worked.
First: Has the Treatment Actually Had a Fair Trial?
Before concluding that antidepressants don't work for you, it's worth checking that they were given a real chance.
- Dose. Many people stay on a starting dose that was never increased. A starting dose is a starting point.
- Duration. Antidepressants take weeks, not days. Stopping at three weeks tells you very little.
- Consistency. Missed doses, or stopping and restarting, change the picture.
- Side effects. If side effects meant you quietly took it less often, that's worth saying out loud. It's extremely common and nobody will be annoyed with you.
None of this is a telling-off. It's the first thing we look at, because a medication that was never properly trialed isn't a medication that failed.
Second: Is the Diagnosis Complete?
This is where a lot of stuck cases turn out to be stuck for a reason.
- Bipolar disorder. The depressed phase of bipolar disorder looks like depression, but antidepressants alone often don't help and can sometimes make things worse. The diagnosis depends on a history of elevated or hypomanic periods, which people rarely bring up unprompted.
- ADHD. Untreated ADHD can produce low mood, demoralization, and exhaustion. Treating the depression without addressing the ADHD leaves half the problem in place.
- Alcohol or substance use. Alcohol in particular works directly against antidepressant treatment, and it's often the part of the history people most want to skip over.
- Medical contributors. Thyroid problems, sleep apnea, chronic pain, and some medications can all sustain depressive symptoms.
- Trauma. Depression that follows unprocessed trauma often needs a different approach than medication alone.
See more: Conditions Treated
A comprehensive psychiatric evaluation exists to find these things. Dr. Charles Shuman is board-certified in both general and addiction psychiatry, which matters when substance use is part of the picture rather than a side issue.
Medication Options That Haven't Been Tried Yet
If the diagnosis holds and the trials were adequate, there's still room in medication before moving on.
Antidepressants come in different classes that work on different systems. Not responding to two drugs in the same class says less than it appears to. Beyond switching, there's augmentation, where a second medication is added to strengthen the first, which is a standard approach in treatment-resistant depression and often more effective than yet another switch.
Pairing medication with psychotherapy also tends to outperform either alone. We provide both here, including cognitive behavioral therapy, acceptance and commitment therapy, mindfulness-based approaches, and existential therapy. You don't need to arrange this with a separate provider.
TMS: Treatment Without Medication
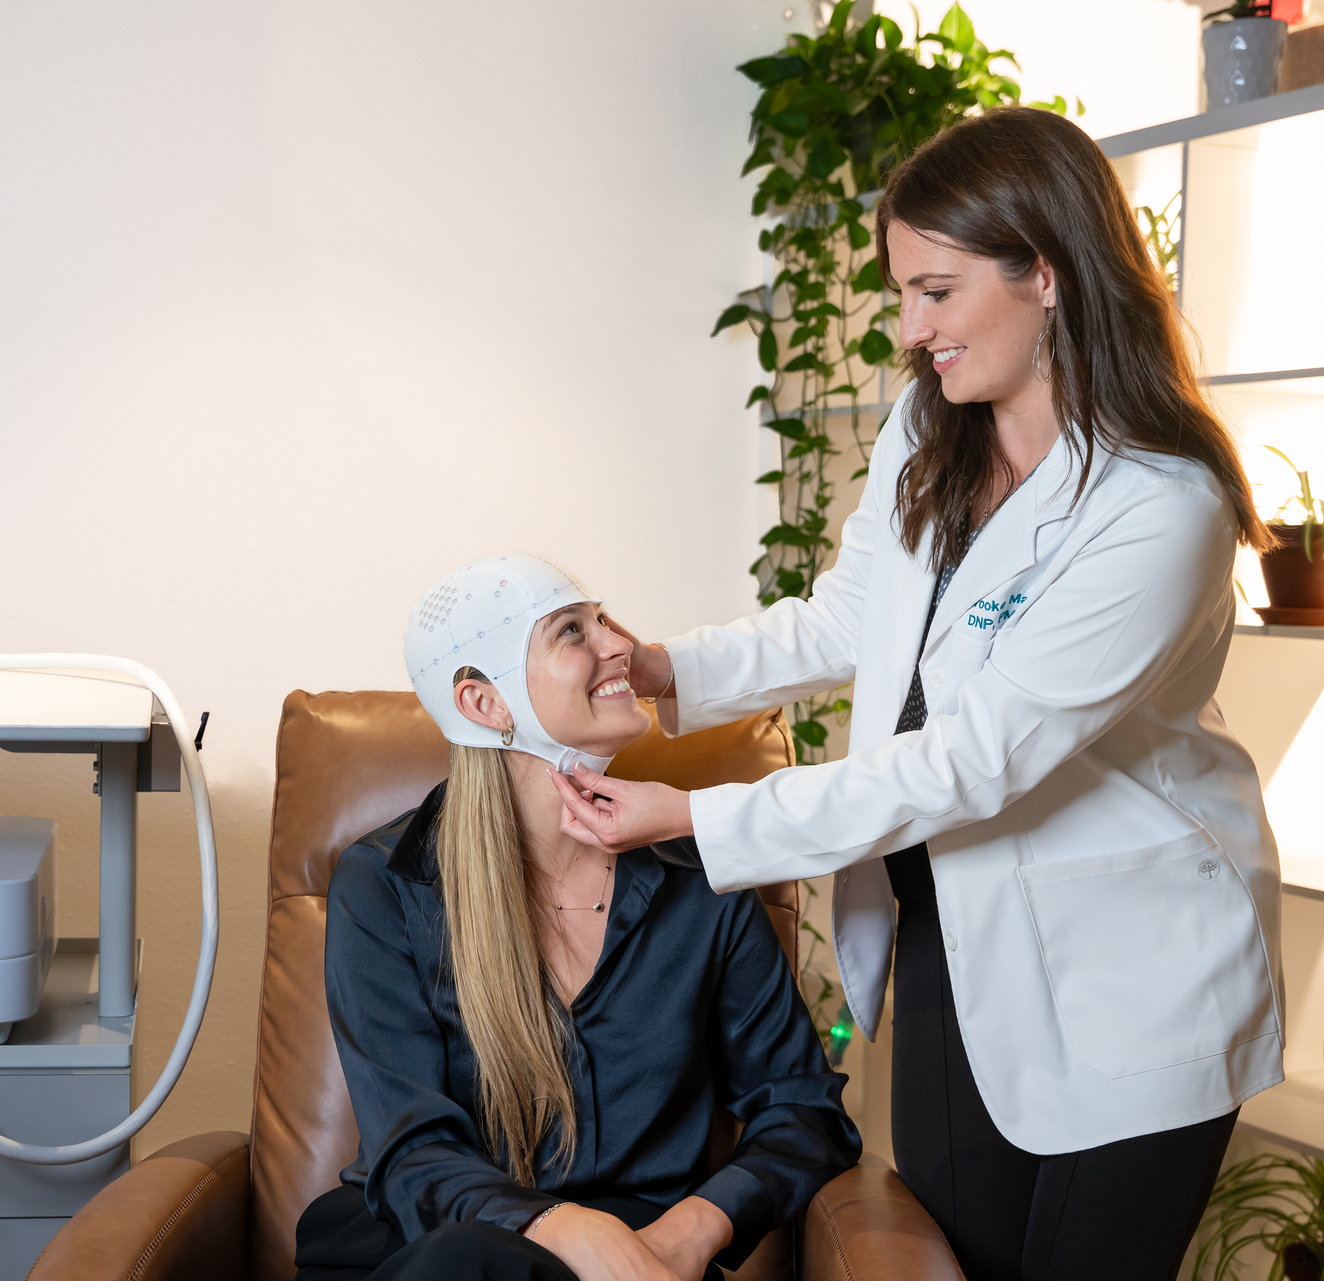
Transcranial magnetic stimulation uses magnetic pulses to stimulate the area of the brain involved in mood regulation. It's FDA-approved for depression and OCD. There's no medication involved, so none of the medication side effects apply, and you stay awake and drive yourself home.
A standard course runs daily over six to eight weeks. Accelerated options compress the same course into five days or two days, which suits people who can't commit to daily appointments or who travel in.
TMS is a strong option specifically for people who responded poorly to medication or couldn't tolerate the side effects.
Not sure what the right next step is?
Every patient starts with a full evaluation with one of our board-certified psychiatrists. We look at what you’ve already tried and what makes sense now.
Spravato and Ketamine: Faster-Acting Options
Ketamine is used off-label for depression and works through a different system than standard antidepressants. Rather than taking weeks, it's associated with a rapid response, and some people notice change within hours or days. We also offer ketamine-assisted therapy, where a therapist is in the room during treatment.
These aren't first-line treatments, and they're not right for everyone. Both start with a full evaluation that covers blood pressure, cardiac history, psychosis history, and substance use history.
What About Insurance?
This is usually the next question, so here it is plainly.
We're in network for TMS and Spravato with Aetna, UnitedHealthcare and Rocky Mountain Health Plans, Medicare through Novitas, TriWest and VA Community Care, and SBA. Some plans, including Cigna, are covered for office visits only. Ketamine is not covered by any insurer and is self-pay everywhere, not just here.
How to Decide Between Them
You don't have to work this out alone, and you shouldn't try to. The decision depends on your history, what's already been tried, your medical background, what your schedule allows, and what you're willing to take on.
What it shouldn't depend on is which treatment a clinic happens to offer. Because medication management, therapy, TMS, Spravato, and ketamine are all provided here by the same psychiatrists, the recommendation can follow your situation rather than the equipment in the building.
Frequently Asked Questions
How long should I give an antidepressant before deciding it isn't working?
Generally several weeks at an adequate dose, but this is a conversation to have with your prescriber rather than a decision to make alone. Don't stop a medication abruptly.
Does trying TMS or ketamine mean stopping my antidepressant?
Usually not. Both are often used alongside existing medication. Your psychiatrist will review what you're taking.
I've tried everything. Is there any point?
"Everything" usually turns out to mean several medications from a narrow range, without augmentation, without therapy alongside, and without TMS or Spravato. A full review is worth having before concluding that nothing works.
Do I need a referral?
No. You can book an evaluation directly.
How quickly can I be seen?
Request an appointment and we'll reply the same day, Monday to Friday, with the current availability.
Latest Posts